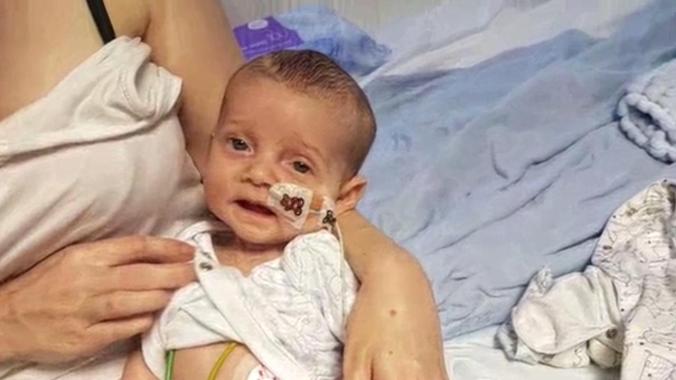
A recipient of Great Britain’s national health care, infant Charlie Gard was born with a rare genetic condition resulting in what is probably irreversable brain damage. He cannot move his arms or legs, eat or even breathe without a ventilator.
After 10 months of being kept alive, Charlie’s caretakers, the Great Ormond Street Hospital for Children in London, announced that it was time for Charlie to die. Chris Gard and Connie Yates, Charlie’s parents, wanted to take him to the United States to try an experimental treatment available here. The doctors at the hospital refused to allow them to take the child, and vetoed their decision, even though the parents had received sufficient funds from donations to pay for the effort. In the resulting lawsuit, British courts sided with the hospital. The parents then brought the case to the European Court of Human Rights, which declined to hear the case last week. The previous court rulings that it was in Charlie’s best interest to withdraw life support and that the state, not the parents, got to make this life and death decision stood.
The parents, Chris Gard and Connie Yates, appeared on a video this week,, sobbing and saying their son would be removed from life support at the hospital. “He’d fight to the very end, but we’re not allowed to fight for him anymore,” Gard said in the video statement. “We can’t even take our own son home to die.”
Initially, the hospital would not delay the fatal disconnection of the child from life support so family members could gather and say goodbye. It has since relented.
Observations: Continue reading







By fortune’s smiles, I was able to finally meet Charlie last week face to face, as he kindly alerted me that he would be passing through my neighborhood. Finally having personal contact with an Ethics Alarms reader is always a revealing and enjoyable experience, and this time especially so. I think you would all enjoy Charlie; I certainly did. Maybe I need to hold an Ethics Alarms convention.
Here is his Comment of the Day on the post, Comment Of The Day: “No, Insurance Companies Treating People With Pre-Existing Conditions Differently From Other Customers Is Not ‘Discrimination’.”
…The claim that “a free market system” and “freedom of choice” is the solution to all that ails us is a mindless mantra that is only occasionally true, but not always.
It’s important to be clear about when free market solutions are good, and when they are not. It’s not all that hard to sort out. Basically:
Free market solutions ought to be the presumptive default. Unless there is good reason to the contrary, they ought to be the rule.
1. Exception Number 1: Natural monopolies. It makes no sense to have competition for municipal water supplies; airports; multiple-gauge railroads; fishing grounds; groundwater; or police departments. The basic reason is the putative economic benefit is either simply not there, or is absurdly overwhelmed by the social confusion engendered by multiple suppliers.
In these cases, a form of regulated monopoly is desirable. (By the way, the airline industry at a national level is precisely this kind of market; we do not have too little competition there, but too little regulation).
2. Exception Number 2a: Wallet-driven market power monopolies. It’s strategy 101 in business schools that the way to be successful is to be #1 or #2, and the best way to do that is to get more market share than your competition, so you can drive them out of business. The one guaranteed way to do that is to cut prices so low that no one else can compete. Think Walmart. Think Amazon. Think Japanese in the 60s and 70s in any industry.
The reason we have anti-monopoly laws is to reset the playing field when a competitor dominates the market too strongly.
3. Exception Number 2b: Product-driven market power monopolies. Where the product is so obscure, expensive, infinitely variable, and difficult to understand that the producers are de facto in control, because it is too confusing and too dangerous to challenge them.
Drug prescriptions are an interesting example. The ‘free market solution’ to high drug prices was (partly) to let drug companies advertise, and to loosen up the definition of what constituted a ‘new’ drug. What did we get? New diseases like RLS, new definitions of ‘new’ (moving ‘off label’ to ‘on label’) and even higher drug company profits. Because who’s still going to argue with your doc? Especially when he or she gets side benefits from giving in to the latest DTC ads on network news programs?
Continue reading →